

Hospitals
Understanding the Clinical Applications of Medical Eye Patches
An authoritative guide for clinicians and procurement heads on the primary medical eye patch uses, including occlusion therapy, post-op care, and evaluation criteria.

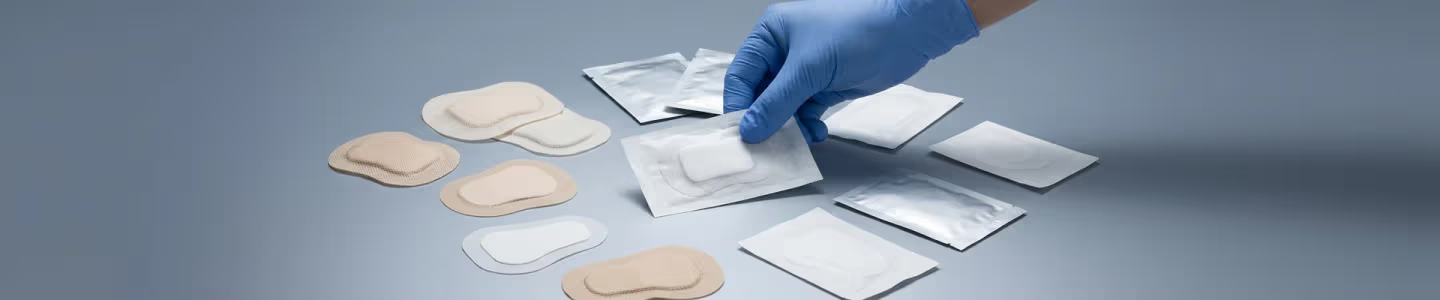
As clinical and operational leads, we deal with a vast inventory of consumables. While some are complex, others, like the humble medical eye patch, are foundational. However, their correct application and selection are critical for patient outcomes, particularly in ophthalmology and paediatrics. Misunderstanding the specific eye patch uses can compromise therapy, delay healing, or lead to patient non-compliance.
This guide moves beyond a basic description to detail the clinical rationale, types, and operational practices for sourcing and using medical eye patches in an Indian healthcare facility. This is not about cosmetic or novelty items, but about a prescribed medical device with specific therapeutic goals.
Core Clinical Applications of Eye Patches
 The primary function of a medical eye patch is either to completely occlude vision in one eye or to provide a protective barrier. These two functions drive its main applications across different departments.
Occlusion Therapy for Amblyopia ("Lazy Eye")
This is perhaps the most critical application of medical eye patches. Amblyopia is a neuro-developmental disorder of vision where an eye fails to achieve normal visual acuity, even with prescription eyewear.
- Mechanism of Action: The core of patch therapy for eye conditions like amblyopia is to cover the "good" or dominant eye. This forces the brain to use and stimulate the neural pathways of the weaker, amblyopic eye, thereby improving its vision over time. This is a classic example of neuroplasticity.
- Patient Population: This therapy is most effective in children, typically up to the age of 7 or 8, as the visual system is still developing.
- Clinical Imperative: The success of eye patch for occlusion therapy is entirely dependent on patient compliance. The patch must be worn for the exact duration prescribed by the ophthalmologist, which could range from two to six hours per day, or more. Incomplete occlusion or inconsistent use will nullify the therapeutic benefit. For these cases, a dedicated orthoptic patch like the 3M Opticlude Orthoptic Eye Patch - Junior 5cm x 6.2cm Pack of 20 (1537) is the clinical standard due to its design for effective occlusion and skin-friendly adhesive.
Post-Surgical and Post-Traumatic Protection
Following ophthalmic surgery (e.g., cataract, vitrectomy, corneal repair) or trauma, the eye is extremely vulnerable.
- Protective Barrier: A patch shields the eye from accidental rubbing, pokes, and foreign bodies like dust. It creates a clean environment immediately over the surgical site, reducing the risk of infection.
- Light Sensitivity (Photophobia): After surgery or injury, patients often experience severe photophobia. An opaque patch provides immediate relief by blocking light.
- Pressure Application: In some post-operative scenarios, a "pressure patch" is applied. This involves layering sterile gauze pads over the closed eye and securing them firmly with medical tape to minimise oedema and bleeding. This is a technique, not a specific product, and must be performed by a trained clinician.
Management of Diplopia (Double Vision)
For patients experiencing temporary or persistent double vision due to cranial nerve palsies, strabismus, or other neurological conditions, occluding one eye offers immediate symptomatic relief. By blocking the input from one eye, the brain receives a single, clear image. This is a palliative measure while the underlying cause of the diplopia is diagnosed and treated.
Corneal Protection
In conditions where the eyelid cannot close fully (lagophthalmos), the cornea is exposed to air and can rapidly dry out, leading to exposure keratitis and ulceration.
- Bell's Palsy: Patients with facial nerve palsy often cannot blink or close their eye. A patch, particularly at night, can help keep the eye closed and protect the cornea.
- ICU/Sedated Patients: Unconscious or heavily sedated patients in the Intensive Care Unit lose their protective blink reflex. Taping the eye shut or applying a patch is a standard nursing protocol to prevent corneal damage.
Types of Medical Eye Patches: An Operational Overview
When sourcing eye patches, understanding the different types and their intended use is essential for matching product to clinical need.
| Patch Type | Description | Primary Use Case | Key Considerations |
| Adhesive Orthoptic Patch | A single-use patch with a hypoallergenic adhesive border and a central non-adherent, light-blocking pad. | Amblyopia (occlusion therapy). | Excellent adhesion, total light occlusion, breathable material, available in paediatric and adult sizes. |
| Non-Adhesive (Reusable) Patch | Typically a fabric or silicone cup held in place by an elastic strap or designed to fit over eyeglasses. | Can be used for diplopia or light sensitivity. Sometimes attempted for amblyopia. | Reusable and economical, but prone to light leakage, easier for children to remove, and may not stay in place. |
| Pressure Patch (Technique) | Not a single product; a combination of sterile gauze pads and medical tape applied firmly. | Post-operative care to reduce swelling and provide firm protection. | Requires clinical skill to apply correctly; must not apply excessive pressure on the globe. |
| Clear Polycarbonate Shield | A rigid, transparent plastic shield, often with perforations for airflow, held by tape or an elastic band. | Post-trauma or post-cataract surgery to protect against physical impact. | Allows for some vision, protects against blunt force, but does not occlude light. |
Procurement and Evaluation Criteria for Your Facility
Selecting the right eye patch isn't about the unit requisition form; it's about clinical efficacy and patient safety. Here's a checklist for evaluating your supply.
- Material and Adhesive Quality:
- Breathability: The patch material must be non-woven and air-permeable. An occlusive plastic material will trap moisture, leading to skin maceration and breakdown, a major cause of non-compliance in children.
- Adhesive: Is the adhesive medical-grade and hypoallergenic? For paediatric occlusion therapy, where a patch is applied and removed daily for months, a gentle adhesive that doesn't cause skin stripping or contact dermatitis is non-negotiable.
- Occlusion Pad: The central pad must be completely opaque to block light effectively. Any light leakage defeats the purpose of amblyopia therapy. It must also be non-adherent so it doesn't stick to the eyelashes or eyelid.
- Sizing and Ergonomics:
- A one-size-fits-all approach is clinically inadequate. Your facility must stock at least two sizes: Junior/Paediatric and Regular/Adult.
- The patch should be anatomically shaped (often oval or "peanut" shaped) to fit comfortably in the orbital area and around the nose bridge without gaping.
- Sterility and Packaging:
- For any post-operative or post-trauma application, patches must be individually wrapped and sterile to prevent surgical site infections.
- For outpatient amblyopia therapy, non-sterile patches in a bulk box may be sufficient, but individual wrapping is always preferable for hygiene.
- Patient Compliance Factors:
- For paediatric use, this is a critical factor. Patches with colourful designs or patterns can transform the experience from a medical chore into something more engaging for a child, dramatically improving adherence.
- The ease and comfort of removal are paramount. If removing the patch is painful, a child will resist its application the next day.
By standardising on high-quality options, you not only ensure better clinical outcomes but also reduce wastage and time spent by clinical staff managing complications like skin irritation. It is crucial to have a reliable inventory to meet these diverse needs. You can Browse Eye patch options to see what fits your facility's requirements.
Correct Way to Apply an Eye Patch: Recommended Practices
Proper application technique ensures the patch is effective, comfortable, and safe. Staff and patient/caregiver education is key.
Step-by-Step Application of an Adhesive Patch:
- Preparation: Start with clean, dry hands. The skin around the patient's eye must also be clean and completely dry. Do not apply any creams or lotions, as they will interfere with the adhesive.
- Positioning: Ask the patient to close both eyes gently without squeezing them shut. This keeps the facial muscles relaxed and prevents wrinkling under the patch.
- Application: Peel the paper liner off the patch. Orient the patch so the narrower end is directed towards the nose. Centre the non-adherent pad over the closed eyelid.
- Securing: Gently lay the patch in place. Do not stretch it. Smooth the adhesive border from the centre outwards to ensure it is firmly sealed against the skin on all sides. A good seal is vital for total light occlusion.
Important Operational Notes:
- Duration (
eye patch lagane ke fayde): The benefits, particularly for amblyopia, are directly tied to duration. The prescribed time (for how much time we should apply eye patch) is a clinical directive and must be followed precisely. It is not optional. - Removal: Do not rip the patch off quickly. Loosen the edges and peel it back slowly and gently, ideally in the direction of hair growth. Supporting the adjacent skin with your fingers can minimise discomfort.
- Skin Integrity: Instruct caregivers to check the skin for any redness or irritation after each use. It's advisable to slightly alter the patch position each day if possible to give the skin a rest.
Equip Your Facility Today
Ensuring a consistent supply of high-quality, clinically appropriate eye patches is a small but significant part of delivering excellent patient care in ophthalmology, paediatrics, and post-operative wards. Evaluating your stock against criteria of material, sizing, and patient comfort ensures your clinicians have the right tools to achieve good outcomes. For your procurement needs, explore the range of medical-grade eye patches available to equip your departments effectively.
FAQs